
What Evidence-Based Trauma Treatment Looks Like
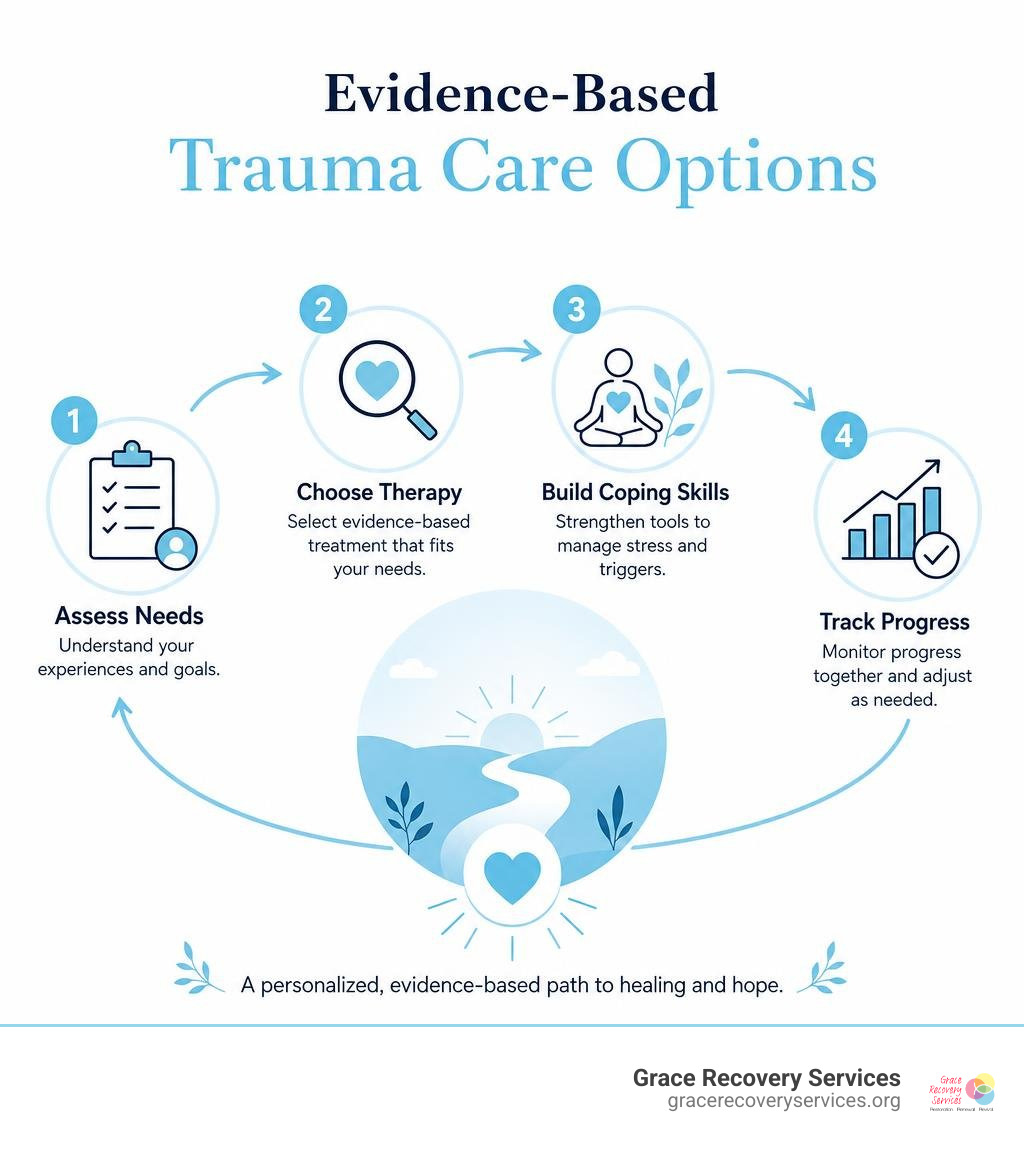
Evidence based trauma treatment means using therapies that have been carefully studied and shown to help people reduce PTSD symptoms and regain daily functioning. For adults with PTSD, the strongest evidence supports trauma-focused therapies such as Cognitive Processing Therapy (CPT), Prolonged Exposure (PE), Eye Movement Desensitization and Reprocessing (EMDR), and trauma-focused CBT.
A practical place to start is:
- Choose a trained, trauma-informed clinician.
- Discuss which evidence-based option feels safest and most workable for you.
- Track progress together and adjust the plan around your goals, recovery needs, culture, and faith.
For clients who are also navigating substance use disorder, trauma care does not have to wait until life is perfect. Research and current VA/DoD guidance support addressing PTSD and substance use together when appropriate, with attention to safety, stability, and personal choice.
At Grace Recovery Services, we recognize that healing involves more than reducing symptoms. It can include rebuilding trust, strengthening healthy relationships, finding supportive coping tools, and reconnecting with hope and purpose. Evidence-based care and Christian compassion can work alongside one another without forcing a client to share more than they are ready to share.
Evidence based trauma treatment word guide:
First-Line Modalities in Evidence Based Trauma Treatment
When evaluating therapies for post-traumatic stress disorder (PTSD), major professional bodies look to rigorous clinical trials. The updated clinical practice guidelines—including the VA/DoD 2023 Clinical Practice Guideline for the Management of PTSD and the expanded 2025 American Psychological Association (APA) guidelines—unanimously place individual trauma-focused psychotherapies at the top of the recommendation list.
Trauma-focused therapies actively process the memories, thoughts, and emotions connected to traumatic events. While standard supportive talk therapy offers comfort, clinical trials show that trauma-focused interventions lead to larger, more enduring symptom reduction.
| Modality | Core Mechanism | Average Duration | Homework Burden |
|---|---|---|---|
| Cognitive Processing Therapy (CPT) | Identifying and modifying trauma-related “stuck points” (guilt, safety, trust) | 12 sessions | Moderate (worksheets and practice exercises) |
| Prolonged Exposure (PE) | In vivo and imaginal exposure to promote natural fear extinction | 8–15 sessions | High (listening to recordings, confronting safe avoided situations) |
| Eye Movement Desensitization and Reprocessing (EMDR) | Processing distressing memories paired with bilateral sensory stimulation | 8–12 sessions | Low (minimal outside homework assignments) |
| Trauma-Focused CBT (TF-CBT) | Cognitive behavioral skills, emotional regulation, and gradual narrative processing | 8–24 sessions | Moderate (family/individual practice) |
Cognitive Processing Therapy in Evidence Based Trauma Treatment
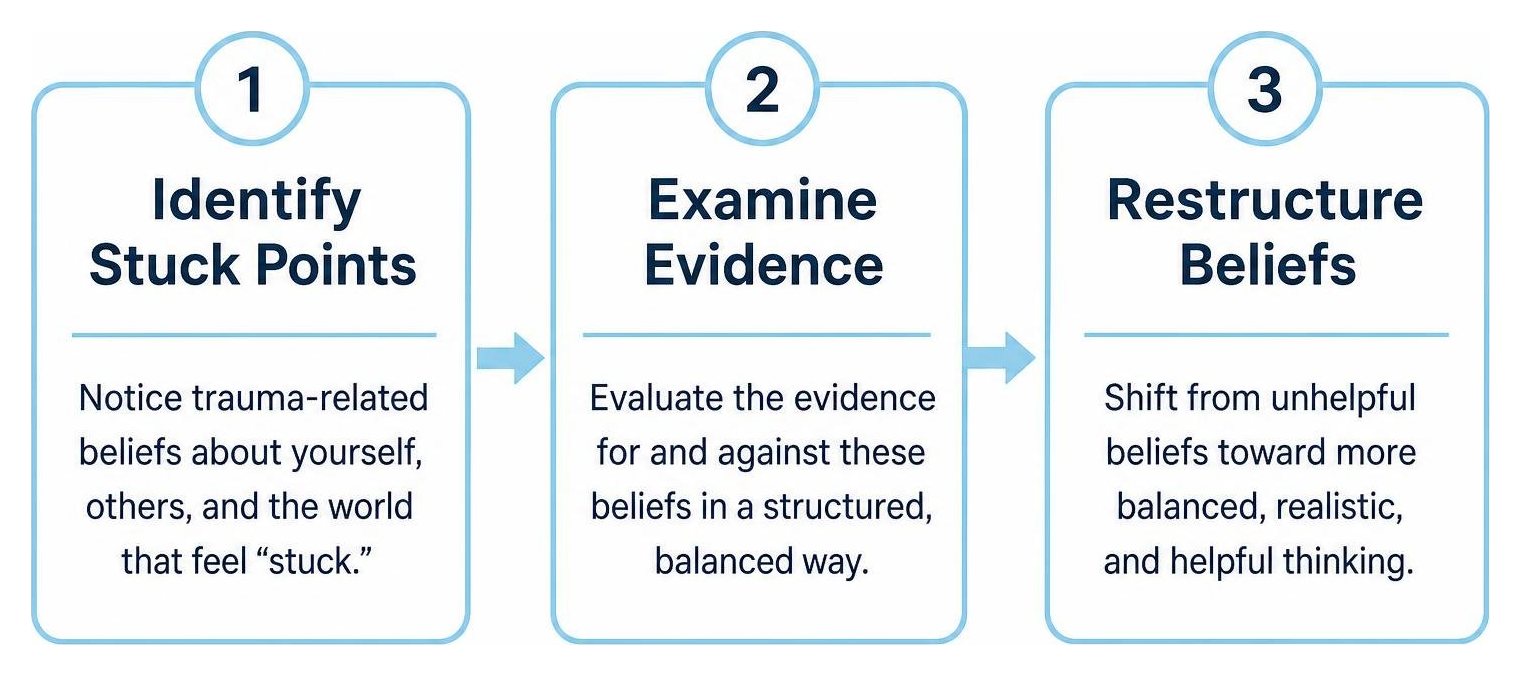
Cognitive Processing Therapy (CPT) operates on the principle that traumatic experiences disrupt how an individual views themselves, other people, and the world. Following distressing events, individuals often develop unhelpful beliefs—known as “stuck points.” These beliefs frequently manifest as self-blame, generalized distrust, or extreme perceptions of danger.
In CPT, clients learn to evaluate their thoughts through structured cognitive restructuring. By examining the evidence for and against these automatic assumptions, individuals gradually shift from rigid self-blame toward balanced truth. Because trauma reactions can look like panic, hypervigilance, or chronic worry, PTSD vs anxiety disorders is an important clinical distinction when mapping out appropriate cognitive targets.
Prolonged Exposure and EMDR Protocols
Prolonged Exposure (PE) is grounded in emotional processing theory. When someone experiences trauma, natural recovery can be blocked by avoiding reminders, thoughts, and feelings related to the event. PE addresses this avoidance directly through two primary methods:
- In Vivo Exposure: Gradually approaching real-world situations, places, or activities that are objectively safe but previously avoided due to trauma triggers.
- Imaginal Exposure: Repeatedly recounting the trauma narrative within a safe clinical setting, allowing the nervous system to learn that the memory itself is not dangerous.

Eye Movement Desensitization and Reprocessing (EMDR) provides an alternative pathway for processing traumatic memories without requiring extensive verbal descriptions. EMDR uses bilateral stimulation—such as side-to-side eye movements, alternating auditory tones, or rhythmic hand taps—while the client holds target memories, negative self-beliefs, and bodily sensations in mind. This dual-attention focus facilitates cognitive reprocessing and lowers physiological arousal.
Second-Line Therapies, Emerging Interventions, and Pharmacotherapy
While first-line therapies provide robust results for many, clinical practice requires alternatives when specific protocols are unavailable, declined, or contraindicated. A comprehensive systematic review on psychological therapies for post-traumatic stress demonstrates that several secondary psychological treatments offer meaningful benefits.
Written Exposure Therapy and Non-Trauma-Focused Options
Written Exposure Therapy (WET) has emerged as a brief, low-burden protocol. Typically completed in just five structured sessions of written exposure with no outside homework, clinical studies show WET achieves symptom reduction non-inferior to longer trauma protocols, accompanied by low client dropout rates.
For clients seeking relief without directly recounting traumatic memories, non-trauma-focused options provide valuable alternatives:
- Present-Centered Therapy (PCT): Focuses on managing current life difficulties and relational challenges related to trauma without delving into trauma narratives.
- Narrative Exposure Therapy (NET): Useful for individuals with complex histories of multiple traumas, helping them contextualize their life story chronologically.
- Mindfulness-Based Stress Reduction (MBSR): Serves as an effective adjunctive practice to improve physiological self-regulation and present-moment awareness.
What Current Guidelines Say About Medications and Psychedelics
Both the VA/DoD and APA guidelines evaluate medications as secondary or adjunctive options rather than primary first-line treatments for PTSD.
- Recommended Antidepressants: When pharmacotherapy is indicated, selective serotonin reuptake inhibitors (SSRIs) like sertraline and paroxetine, as well as the SNRI venlafaxine, have the strongest clinical support.
- Nightmare Management: Prazosin is frequently utilized off-label to address trauma-related nightmares and sleep disruption.
- Medications Recommended Against: Clinical guidelines strongly advise against using benzodiazepines or cannabis products for PTSD. Benzodiazepines interfere with natural fear extinction learning and carry significant risks of physical dependence.
- Emerging Interventions: While research into MDMA-assisted therapy and ketamine continues to evolve, current guidelines conclude there is insufficient high-quality, unbiased evidence to recommend them for standard clinical PTSD care.
Complex PTSD, Self-Regulation, and Trauma-Informed Integration
Complex PTSD (CPTSD), officially recognized in the World Health Organization’s ICD-11, includes standard PTSD symptoms alongside persistent disturbances in self-regulation:
- Affect Dysregulation: Marked difficulties managing intense emotional surges, anger, or numbness.
- Negative Self-Concept: Deep-seated feelings of worthlessness, shame, or failure.
- Relational Difficulties: Persistent challenges sustaining close, secure interpersonal relationships.
Navigating these challenges requires a solid foundation in trauma-informed care, ensuring clinical environments foster physical, emotional, and psychological safety. Clinicians frequently reference the VA/DoD Clinical Practice Guideline for the Management of PTSD Quick Reference Guide when tailoring interventions.
Adapting Evidence Based Trauma Treatment for Complex Trauma
For decades, clinicians operated under the assumption that individuals with complex trauma required lengthy, multi-year stabilization phases before initiating trauma processing. However, recent empirical findings indicate that delaying trauma-focused therapy often increases treatment dropout. Most clients benefit from moving directly into structured, evidence-based trauma therapy, provided immediate safety and basic stability are present.
Modern delivery models have also expanded access. Evidence confirms that delivering trauma treatments via secure video teleconferencing yields comparable outcomes to in-person sessions, removing travel barriers for clients balancing work, family, or transportation constraints.

Treating Co-Occurring Substance Use and Trauma
Unresolved traumatic stress often drives substance use as an attempt to self-medicate distressing memories, nightmares, and chronic hyperarousal. Historically, individuals were told they had to achieve extended sobriety before addressing their trauma. Today, clinical guidelines emphasize concurrent, integrated care.
Integrated protocols—such as Concurrent Treatment of PTSD and Substance Use Disorders Using Prolonged Exposure (COPE)—safely address trauma and substance use simultaneously. Integrating evidence-based addiction treatment with trauma processing reduces relapse triggers and supports lasting recovery.
Clients exploring outpatient options can learn more about all about trauma-informed addiction treatment options and reference a clear step-by-step guide to healing from addiction and trauma to navigate their journey.
Integrating Whole-Person, Faith-Based, and Holistic Healing
At Grace Recovery Services, we deliver evidence-based clinical protocols through our structured Counseling Blueprint, which guides clients across four intentional stages:
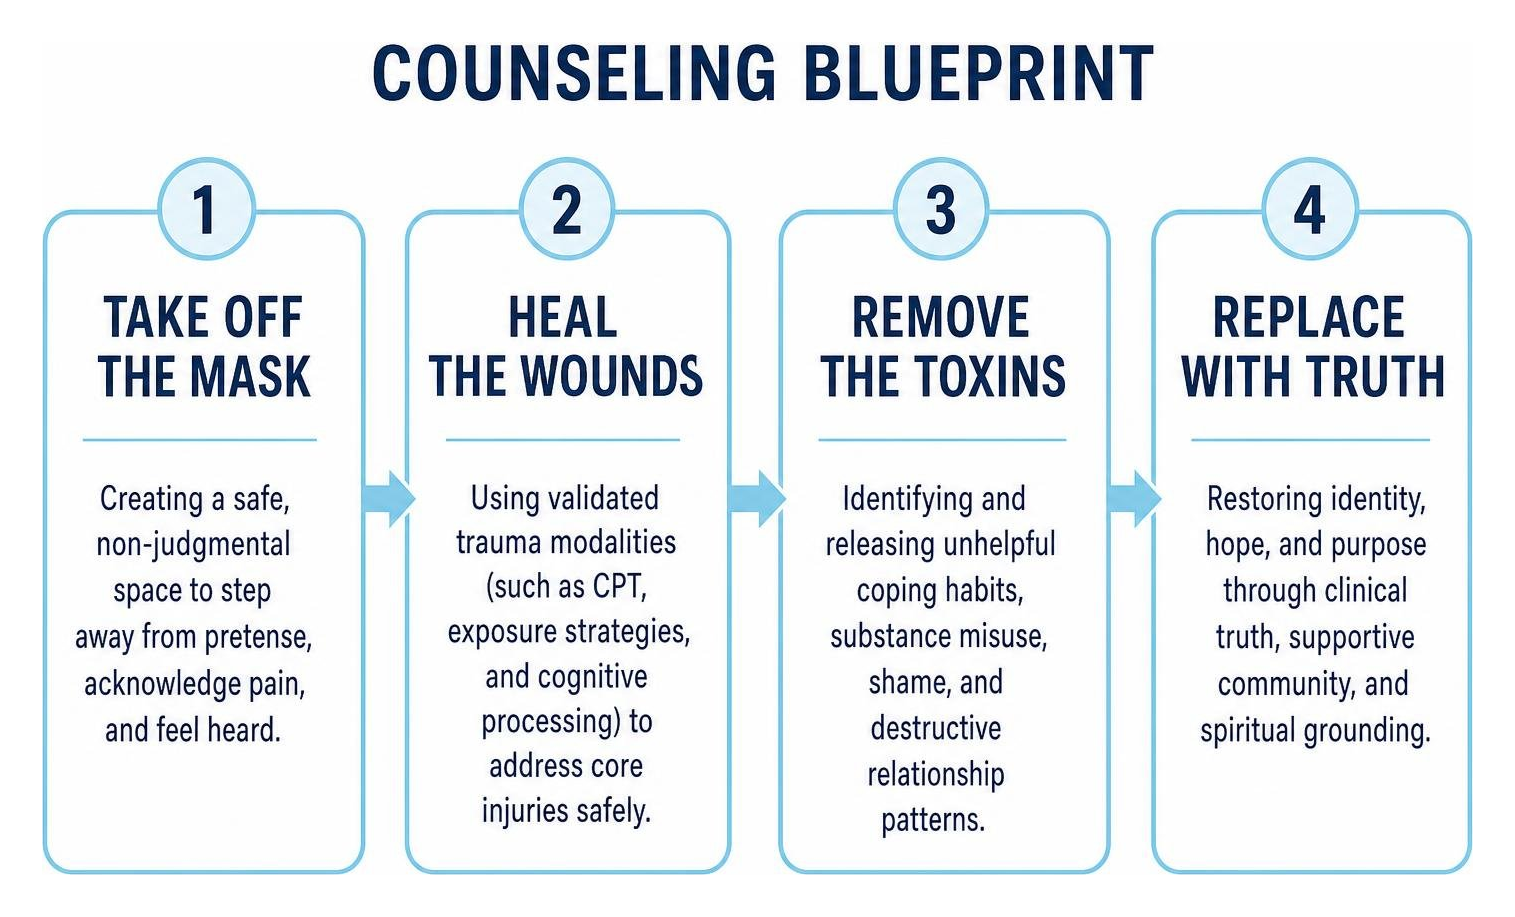
- Stage 1: Take Off the Mask — Creating a safe, non-judgmental outpatient space where clients can step away from pretense, acknowledge their pain, and feel genuinely heard.
- Stage 2: Heal the Wounds — Utilizing validated trauma modalities (such as CPT, exposure strategies, and cognitive processing) to address core injuries safely.
- Stage 3: Remove the Toxins — Identifying and releasing unhelpful coping habits, substance misuse, shame, and destructive relationship patterns.
- Stage 4: Replace with Truth — Restoring identity, hope, and purpose through clinical truth, supportive community, and spiritual grounding.
Combining clinical rigor with faith-based trauma recovery allows individuals to draw on their spiritual beliefs as a source of strength, hope, and resilience. Exploring why your trauma needs a holistic approach to healing ensures that the physical, emotional, and spiritual aspects of a person are fully nurtured.
Frequently Asked Questions About Evidence-Based Trauma Care
Is psychotherapy more effective than medication for trauma?
Yes. Large-scale clinical meta-analyses demonstrate that trauma-focused psychotherapies (such as CPT, PE, and EMDR) produce greater symptom reduction and more durable, long-term recovery than medications alone. While medications can help alleviate acute distress, psychotherapy equips individuals with lasting cognitive and emotional tools.
Is a lengthy stabilization phase required before starting trauma therapy?
Not typically. Modern research demonstrates that clients with complex trauma, dissociation, or co-occurring concerns can safely begin evidence-based trauma therapies without months of preliminary stabilization, provided they are not in immediate crisis. Direct engagement in structured therapy often leads to faster relief and lower dropout rates.
Can someone with a substance use disorder receive trauma-focused therapy?
Absolutely. Clinical guidelines explicitly state that a co-occurring substance use disorder should not disqualify someone from receiving first-line trauma therapies. Integrated care addresses substance use and trauma concurrently, preventing unaddressed trauma from fueling future relapse.
Finding Hope and Healing in Western Pennsylvania
Recovery from traumatic experiences is entirely possible with the right clinical care, supportive relationships, and personal commitment. You do not have to carry the weight of past distress or navigate co-occurring substance use alone.
If you are exploring local outpatient care, resources like finding the best Western PA trauma rehab for your needs can help clarify your options. Grace Recovery Services provides outpatient clinical care, compassionate Christian counseling, and intensive outpatient support across our offices in Penn Hills (Pittsburgh area) and North Huntingdon in Westmoreland County.
Whether you are seeking individual outpatient therapy or looking into our North Huntingdon Christian intensive outpatient program, our team is dedicated to walking alongside you with clinical excellence and Christian grace. We invite you to contact Grace Recovery Services today for a personalized, confidential assessment and take your next step toward lasting healing.
This article was researched with AI and heavily edited by Stephen Luther for accuracy and relevance.
Stephen Luther is the Executive Director and Founder of Grace Christian Counseling, Grace Recovery Services, WPA Counseling, NuWell Online Counseling and Coaching, and NuWell Health. He holds a Master’s degree in Education from the University of Georgia and a Master’s degree in Marriage and Family Therapy from Duquesne University. He is a licensed professional counselor in Pennsylvania.
Since 1997, Steve has been helping children, adolescents, and adults overcome a wide range of emotional and relational challenges. He specializes in working with hurting families, including those with foster, adopted, or traumatized children. Steve uses Attachment-Based Therapy, Splankna Healing, and Therapeutic Parent Coaching to support healing and restoration.
This guide is for educational and spiritual encouragement and is not a substitute for personalized professional counseling. If you are in crisis, please reach out for immediate help.