

What “co-occurring” means
A co-occurring condition is a substance use disorder and a mental health disorder present in the same person.[1] Only a qualified professional can diagnose either condition. Someone can also have significant symptoms that deserve attention before a diagnosis is clear. Sleep disruption, panic, depressed mood, racing thoughts, or difficulty concentrating may affect treatment participation, but an online article cannot determine what those symptoms mean.
The relationship between substance use and mental health can be complicated. A person may use alcohol or another drug while trying to cope with distress. Substance use may also intensify or resemble some psychiatric symptoms. Both concerns may arise from shared biological, psychological, relational, social, or environmental factors.[3] It is safer and more accurate to assess the pattern than to assume one condition caused the other.
Trauma may be an important part of a person’s story, but trauma does not cause every addiction. Trauma-informed care should emphasize safety, trust, choice, collaboration, and pacing. It should not require someone to disclose painful experiences or begin deeper trauma processing before adequate safety and stability are present. If trauma is part of your decision, our guide on how to evaluate trauma-informed addiction treatment offers questions to ask.
What integrated treatment for addiction and mental health should coordinate
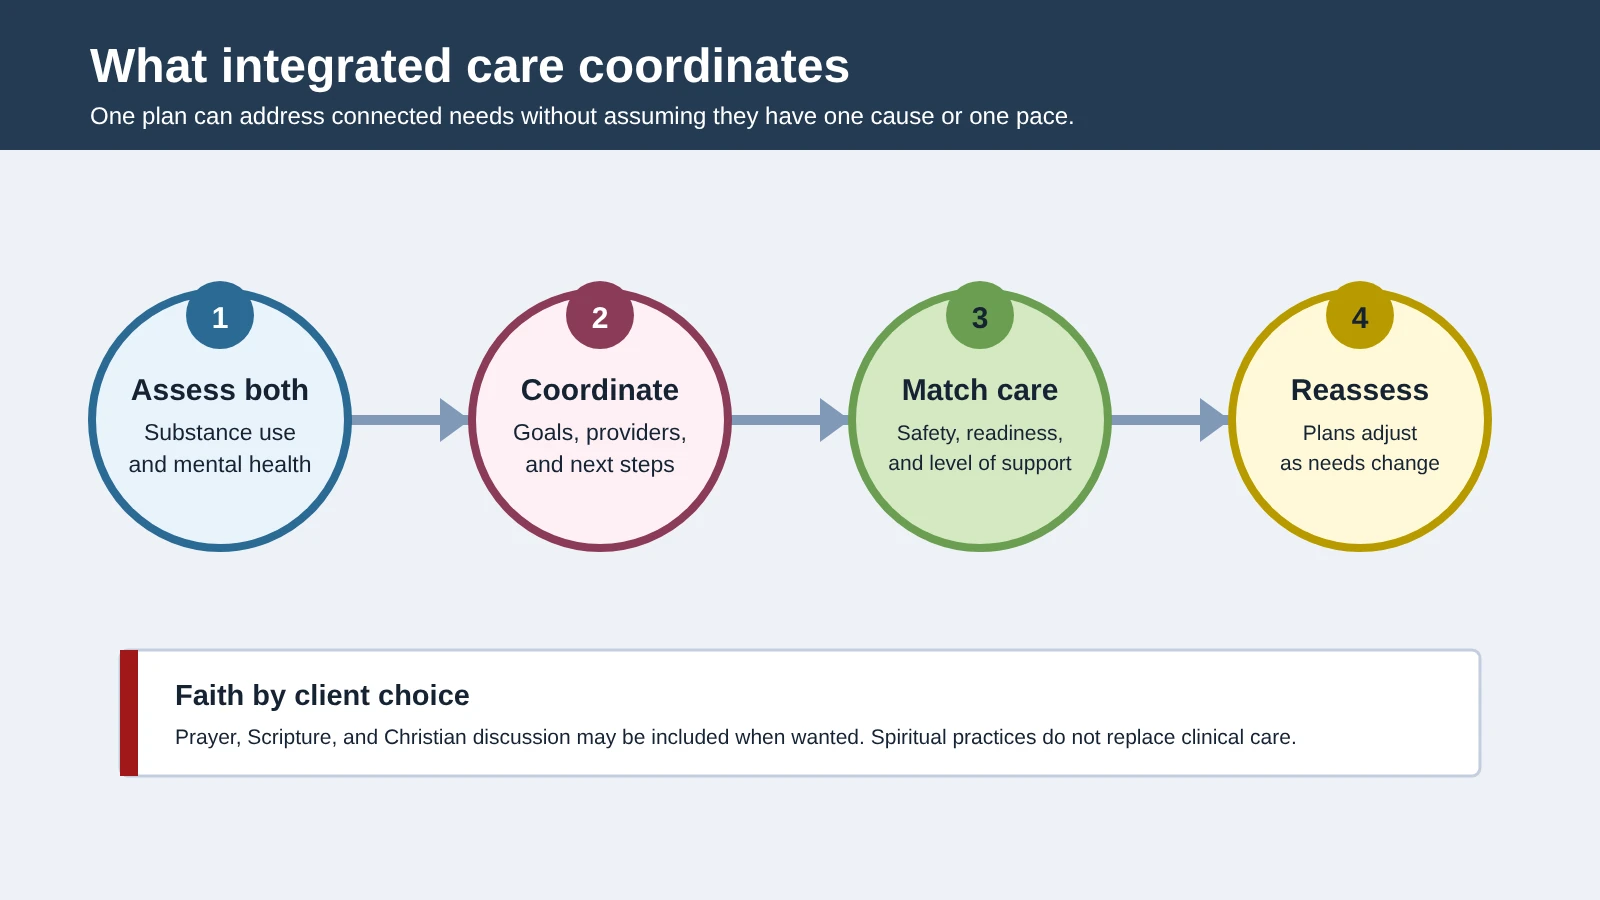
SAMHSA describes integrated care as a unified approach to substance use, mental health, and related needs.[1][2] Its guidance for treatment providers also recommends screening people who seek substance use care for mental health concerns, and screening people in mental health care for substance use. In practice, the details vary by setting and by the person’s current needs. A credible program should be able to explain which services it provides directly, what it coordinates with outside professionals, and what requires a different level of care. For GRS program details, see our program page for co-occurring care.
Co-occurring treatment starts with assessing both areas
One understandable plan
Care matched to safety and readiness
Reassessment over time
How symptoms may affect each other without a simple “root cause” story
People often want a clear explanation for what is happening. A simple story can feel reassuring, but it can also hide important differences. Anxiety can precede substance use, follow it, or change with intoxication or withdrawal. Depression can affect motivation and connection, while substance use can deepen isolation or disrupt sleep. Trauma-related reactions may shape trust and participation, but not every person with addiction has a trauma history, and not every painful experience needs immediate processing.
Integrated treatment for addiction and mental health asks practical questions: What is happening now? What creates immediate risk? What helps the person participate safely? Which symptoms need diagnostic clarification? What support is available between appointments? This keeps the focus on the person rather than forcing every experience into one explanation.
Assessment and level of care in co-occurring treatment
Integrated treatment for addiction and mental health does not mean outpatient care is right for everyone at every moment. A professional assessment may consider withdrawal risk, overdose history, suicidal thoughts, severe psychiatric symptoms, medical needs, living environment, transportation, ability to attend, and support outside sessions. A person may need more intensive or medically supported care before outpatient treatment is considered. A referral to another service is not a rejection. It is part of matching care to current needs.
What co-occurring treatment may look like in an outpatient setting
When outpatient care is clinically appropriate, co-occurring support may include scheduled counseling, skills for coping with cravings and emotions, relapse-prevention planning, attention to relationships and daily routines, coordination with medical or psychiatric providers, and review of symptoms that affect participation. The exact mix depends on program scope and the individual plan. Ask who is qualified to diagnose, who can prescribe medication, how the program coordinates outside care, and what happens when needs exceed the program’s capabilities.
Medication may be part of care for a substance use disorder, a mental health condition, or both. No recovery group or faith community should tell someone to stop prescribed medication. Those decisions belong with a qualified prescriber who knows the person’s history and current care.
A standard outpatient program generally involves less structure than an intensive outpatient program. Neither label tells you everything about quality or fit. Ask about the current schedule, service availability, assessment procedures, clinician qualifications, crisis boundaries, confidentiality, and how the program changes a plan when risk increases or progress stalls. Family members can receive general education and support, but they do not automatically receive information about an adult client’s treatment. That depends on consent, clinical appropriateness, and privacy rules.
Christian faith can be included without replacing professional care
Christian faith is central to Grace Recovery Services and shapes its understanding of dignity, grace, hope, truth, and restoration. When a client wants faith included, care may make room for prayer, Scripture, or Christian discussion. People are welcome to inquire regardless of belief, and each client chooses whether and how to participate in spiritual practices. Learn more about our approach to faith-based recovery.
Questions to ask a co-occurring treatment program
- How do you screen and assess both substance use and mental health concerns?
- Which co-occurring needs can your program address directly, and which require referral or coordination?
- How do you determine whether outpatient care is safe and appropriate right now?
- What happens if withdrawal risk, suicidal thoughts, severe symptoms, or another urgent concern emerges?
- Who is qualified to diagnose, provide therapy, or prescribe medication?
- How do providers communicate, and what consent is needed before information is shared?
- How does trauma-informed care show up in safety, choice, pacing, and boundaries?
- If I want Christian faith included, what might that look like? If I do not, how will the team respect that choice?
- How often does the team reassess the treatment plan?
How Grace Recovery Services approaches co-occurring treatment
A care-team conversation can review current needs and available options, but contacting GRS does not guarantee admission, a particular program, a start date, or a clinical outcome.
Grace Christian Counseling may be an additional or continuing counseling option when appropriate. It is a separate service path, not automatic enrollment, a shared admission, or a promise that every need can be handled within one organization. Ask the GRS care team to confirm current coordination, program availability, location, insurance participation, payment options, and whether telehealth is available for your needs and location. Professionals helping an adult explore care can review our guidance for outpatient addiction treatment referrals near Pittsburgh.
Frequently asked questions
Does “co-occurring” mean one condition caused the other?
No. Substance use and mental health concerns can influence each other, share risk factors, or occur for different reasons. A qualified professional should assess the pattern rather than assuming a single cause.
Does integrated care mean one therapist provides every service?
Not necessarily. Integrated care means the plan is coordinated. Some services may come from one team, while medical, psychiatric, or specialty care may involve other providers with appropriate consent and communication.
Can outpatient treatment address every co-occurring need?
No. Outpatient care is one part of a broader continuum. Emergency care, withdrawal management, inpatient or residential services, medication management, or other specialty treatment may be needed depending on current risk and clinical needs.
Is integrated treatment the same as dual diagnosis treatment?
The terms are often used for care that addresses a substance use disorder and a mental health disorder together. “Co-occurring disorders” is the more current term. Ask a provider what services are actually included, because a program name alone does not show how care is coordinated.
Do I need two confirmed diagnoses before I ask for help?
No. You can ask for an assessment when substance use and mental health symptoms are both affecting your life. A qualified professional can help clarify what needs attention, what may need further evaluation, and which level or type of care may fit.
Do I have to be a Christian to contact GRS?
No. Christian faith is central to GRS, but people are welcome to inquire regardless of belief. Prayer, Scripture, and other spiritual practices are guided by client choice and do not replace clinical care.
Sources
- 1Advisory: Substance Use Disorder Treatment for People With Co-Occurring Disorders (based on TIP 42). Substance Abuse and Mental Health Services Administration.
- 2TIP 42: Substance Use Treatment for Persons With Co-Occurring Disorders. Substance Abuse and Mental Health Services Administration.
- 3Co-Occurring Disorders and Health Conditions. National Institute on Drug Abuse.
- 4Mental Health and Substance Use Helplines (including the National Helpline and 988). Substance Abuse and Mental Health Services Administration.
